Why Do My Ears Feel Full and Muffled Suddenly?

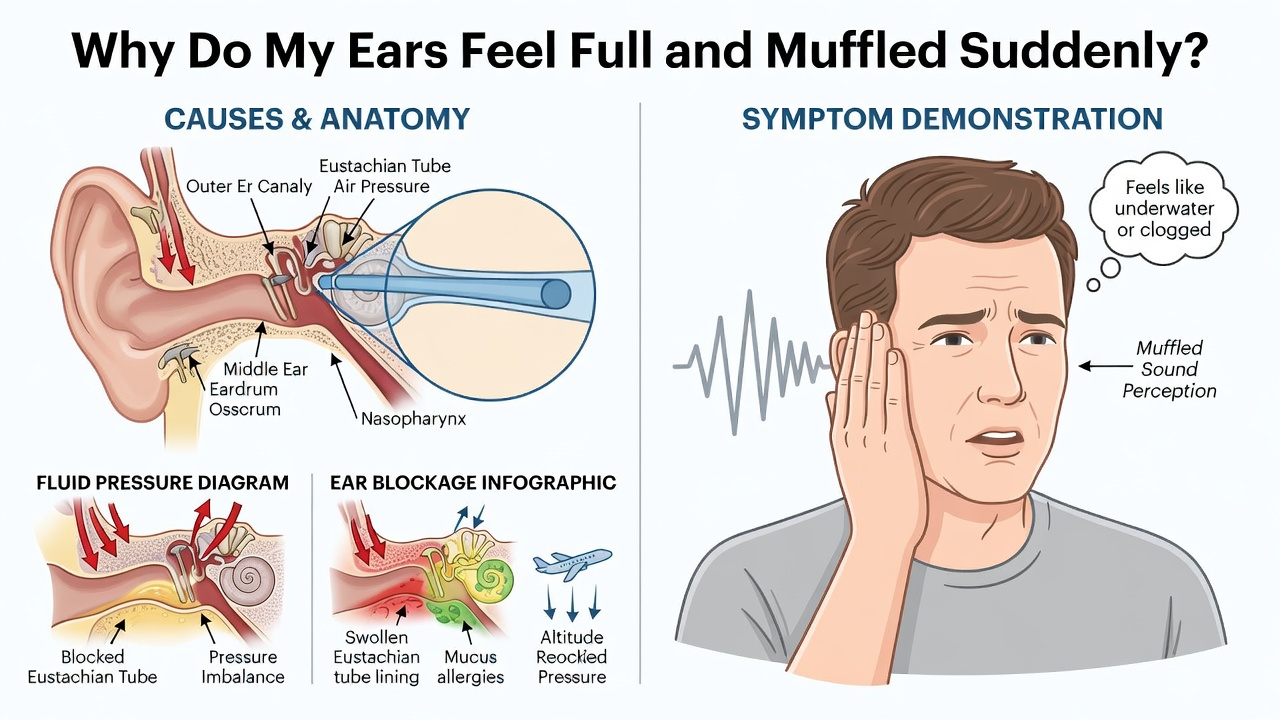
That sudden sensation of pressure, fullness, or muffled sound in one or both ears can be unsettling — and it happens to millions of people every year. Whether it comes on while you are driving up a mountain, waking up with a cold, or simply sitting at your desk, the experience almost always raises the same question: why do my ears feel full and muffled suddenly?
The short answer is that the feeling of ear fullness — clinically called aural fullness — most commonly results from a disruption in the pressure-equalising system of the middle ear, a blockage in the outer ear canal, or a sudden change in inner ear fluid dynamics. While the sensation is often harmless and resolves on its own, some causes require prompt medical attention. Understanding the difference could protect your long-term hearing.
This article walks through every major cause of sudden ear fullness and muffled hearing, explains the underlying anatomy, outlines red-flag symptoms you should never ignore, and offers evidence-based guidance on what you can do right now.
How the Ear Maintains Clear Hearing
To understand why ears suddenly feel full, it helps to know the basic anatomy. The ear has three compartments: the outer ear canal, the middle ear (an air-filled space behind the eardrum), and the fluid-filled inner ear. The Eustachian tube connects the middle ear to the back of the throat, and its primary job is to equalise air pressure on both sides of the eardrum.
When anything disrupts the free movement of sound vibrations — a pressure imbalance, a blockage, excess fluid, or abnormal nerve signals — the result is the characteristic muffled, underwater, or plugged sensation. Even a small obstruction in this finely tuned system can noticeably reduce sound clarity, create balance problems, and cause a sense of pressure or congestion inside the ear.
Eustachian Tube Dysfunction: The Most Common Culprit
Eustachian tube dysfunction (ETD) is by far the most frequent reason ears feel suddenly full and muffled. When the tube fails to open or close properly, air pressure in the middle ear becomes unequal relative to the outside environment. The eardrum is then pulled slightly inward or pushed outward, dampening vibration and producing that familiar blocked feeling.
ETD is often triggered by upper respiratory infections, seasonal allergies, sinus congestion, or sudden altitude changes such as flying or driving over a mountain pass. Swallowing, yawning, or performing a gentle Valsalva manoeuvre (pinching the nose and blowing gently) can temporarily open the tube and relieve pressure. Research published in a study in the journal Otolaryngology–Head and Neck Surgery confirmed that ETD affects a significant proportion of the adult population and is a primary driver of middle ear complaints.
Chronic ETD that persists beyond a few weeks may require nasal steroid sprays, antihistamines, or in some cases a specialist procedure called balloon Eustachian tuboplasty to restore normal function.
Earwax Impaction: A Simple but Overlooked Cause
Cerumen — the medical term for earwax — is a naturally produced substance that protects the ear canal from dust, bacteria, and debris. In most people it migrates outward on its own, but in others it can accumulate and harden into an impaction that physically blocks sound transmission. The result is a sudden or gradually worsening sense of fullness and muffled hearing, sometimes accompanied by mild pain, itching, or ringing.
Ironically, cotton swabs are one of the leading causes of earwax impaction because they push wax deeper into the canal rather than removing it. A study in the American Family Physician journal estimated that earwax impaction affects up to 6% of the general population and is among the most common ear complaints presenting to primary care.
Irrigation with warm water, softening drops containing carbamide peroxide, or professional microsuction by a clinician are the safest and most effective removal methods. The National Institute on Deafness and Other Communication Disorders (NIDCD) provides clear guidance on safe earwax management.
Sudden Sensorineural Hearing Loss: A Medical Emergency
One cause of sudden ear fullness and muffled hearing that demands urgent attention is sudden sensorineural hearing loss (SSNHL). This condition is defined as a rapid loss of 30 decibels or more of hearing across three contiguous frequencies. Patients may also develop tinnitus and ringing in the ears as accompanying symptoms. Patients often describe waking up one morning to find one ear sounding as if it is packed with cotton wool, sometimes accompanied by tinnitus (ringing) or dizziness.
SSNHL is considered an otological emergency. Early treatment with high-dose oral or intratympanic corticosteroids significantly improves the chance of partial or full hearing recovery. A landmark study published in Otology and Neurotology demonstrated that intratympanic steroid injection offers comparable outcomes to systemic steroids with fewer side effects, and current guidelines recommend initiating treatment as soon as possible after onset.
If your ear suddenly becomes muffled with no obvious cause such as congestion or a plane flight, and the sensation does not clear within 24 to 48 hours, seek medical evaluation immediately. Delays of more than two weeks in starting treatment substantially reduce the likelihood of recovery.
Fluid in the Middle Ear (Otitis Media with Effusion)
Sometimes called "glue ear," otitis media with effusion (OME) occurs when non-infected fluid accumulates behind the eardrum. While it is especially common in children, adults can develop OME following a respiratory infection, an episode of ETD, or rapid pressure changes. The fluid dampens eardrum vibration and produces a persistent sensation of fullness alongside muffled hearing, though usually without significant pain.
Most cases in adults resolve spontaneously within four to twelve weeks. A study in the Archives of Otolaryngology found that watchful waiting combined with nasal autoinflation devices (such as the Otovent balloon) can accelerate resolution by helping reopen the Eustachian tube. Persistent OME lasting more than three months typically warrants referral to an ear, nose, and throat specialist.
Ménière's Disease and Inner Ear Fluid Imbalance
Ménière's disease is a disorder of the inner ear caused by abnormal regulation of the fluid (endolymph) within the membranous labyrinth. Classic attacks involve a triad of episodic vertigo (often described as sudden dizziness and nausea), fluctuating low-frequency hearing loss, and aural fullness — often with tinnitus. The fullness sensation frequently arrives as a warning sign before a vertigo episode and can last from minutes to several hours.
Although the exact cause of endolymphatic hydrops remains debated, contributing factors include immune dysregulation, viral infection, and impaired endolymph reabsorption. A study in the Journal of Neurology, Neurosurgery and Psychiatry noted that MRI with intratympanic gadolinium can now visualise endolymphatic hydrops directly, improving diagnostic accuracy. Management includes low-sodium diet, diuretics, betahistine, and in refractory cases, intratympanic gentamicin or endolymphatic sac surgery.
Other Notable Causes of Sudden Ear Fullness
Temporomandibular joint (TMJ) dysfunction is an often-overlooked cause of aural fullness. Because the TMJ sits directly in front of the ear canal and shares nerve supply with middle ear structures, jaw inflammation or misalignment can create referred pressure sensations in the ear. Patients may notice the fullness worsens when chewing, yawning, or clenching the jaw.
Acoustic neuroma (vestibular schwannoma) is a benign tumour on the vestibulocochlear nerve that can cause unilateral muffled hearing and fullness, often progressing slowly over months to years. Any unilateral, unexplained, or asymmetric hearing change should be investigated with an MRI of the internal auditory canals to rule this out.
Noise-induced hearing damage after exposure to loud concerts, power tools, or explosions can produce temporary threshold shift — a temporary form of muffled hearing and fullness that usually resolves within 16 to 48 hours. Repeated temporary threshold shifts accumulate into permanent damage over time, making hearing protection essential.
Certain medications — including loop diuretics, high-dose aspirin, some antibiotics such as gentamicin and streptomycin, and chemotherapy agents like cisplatin — are ototoxic and can cause acute hearing changes. If ear fullness or muffled hearing begins shortly after starting a new medication, contact your prescribing clinician promptly.
Red-Flag Symptoms: When to Seek Immediate Help
Most cases of sudden ear fullness resolve within a few hours to a few days and do not indicate a serious problem. However, certain accompanying symptoms should prompt same-day or emergency medical evaluation:
- Sudden one-sided hearing loss with no clear trigger (possible SSNHL — treat as emergency)
- Severe vertigo — spinning sensation lasting more than 20 minutes
- Facial weakness or numbness on the same side as the affected ear
- Ear pain with fever and discharge — may indicate acute otitis media or outer ear infection
- Sudden fullness following head trauma — could indicate a perilymph fistula or temporal bone fracture
- Symptoms that persist beyond 2 weeks without any improvement
What You Can Do Right Now
If the fullness appeared after a flight or altitude change, try swallowing repeatedly, chewing gum, or performing the Valsalva manoeuvre — these actions gently open the Eustachian tube and typically resolve pressure-related fullness within minutes. Nasal decongestant sprays used for no more than three days can also help if significant congestion is contributing.
If you suspect earwax build-up, commercially available carbamide peroxide drops can soften the wax over several days before gentle irrigation. Avoid cotton swabs and ear candles, which carry significant risks of further impaction or injury to the ear canal and eardrum.
For allergy-related fullness, a non-drowsy antihistamine or intranasal corticosteroid spray may provide relief within a few days. Staying well-hydrated and managing nasal inflammation are key steps in preventing recurrent episodes linked to ETD.
Most importantly, if there is any uncertainty about the cause — especially if hearing is clearly reduced in one ear — arrange an audiological evaluation. A pure-tone audiogram takes only about 20 minutes and can immediately distinguish between conductive and sensorineural hearing changes, guiding the most appropriate next steps.
Frequently Asked Questions
Scientific References
Editorial Information
Sarah Mitchell writes educational content covering health, nutrition, and wellness topics. Her work is intended to present information in a clear and accessible format while encouraging readers to consult qualified healthcare professionals for personal medical advice.